A small cut, blister, or pressure spot can become serious when reduced sensation, poor blood flow, infection, or repeated walking keeps it from healing. You will learn how to triage the wound, protect it during the first day, understand the tests and treatments clinicians use, and choose follow-up that measures real progress.
Key takeaways
- Seek same-day care for spreading redness, swelling, pus, foul odour, black tissue, or red streaks.
- Ask the clinician to assess blood flow, sensation, pressure, infection, and the wound’s depth.
- Pressure relief protects healing tissue; a dressing alone cannot correct repeated friction or weight-bearing.
- Compare services by wound assessment, infection testing, imaging access, offloading, and follow-up plans.
Which diabetic foot wounds need medical attention today?
A diabetic foot wound needs same-day assessment when redness spreads, the skin feels warm or swollen, pus or foul odour appears, tissue turns black, red streaks travel up the foot or leg, pain increases, or a new wound develops over a bony prominence.
Neuropathy can remove protective pain, so a deep, painless ulcer is not reassuring. This is central to diabetic wound care in Pune.
During the first 24 hours:
- Rinse the wound gently with clean running water.
- Cover it with a sterile, non-stick dressing.
- Avoid walking on the injured foot.
- Do not apply peroxide, alcohol, or turmeric, and do not cut away dead skin at home.
| Seek same-day assessment | Seek emergency care now |
|---|---|
| Spreading redness, warmth, swelling, pus, foul odour, black tissue, red streaks, increasing pain, or a new wound over a bony prominence | Fever with severe illness, confusion, or suspected sepsis |
| Any wound that deepens, drains, or worsens despite keeping it covered | Rapidly spreading redness, exposed bone, or rapidly increasing swelling |
| A painless ulcer in an area with reduced sensation | A cold or pale foot, which can signal critically reduced blood flow |
Do not wait for a routine appointment when emergency signs are present. Arrange urgent evaluation, keep weight off the foot, and take your medicines and glucose record with you.
How does a clinician determine what is causing the wound?
The first clinical task is to identify whether the wound is neuropathic, ischemic, infected, pressure-related, or linked to Charcot foot. These causes can coexist, so a painless ulcer still needs assessment; neuropathy can remove protective sensation while poor blood flow, pressure, or infection continues damaging tissue.
The clinician records:
- Length, width, depth, undermining, tissue type, and drainage
- Callus, pressure points, deformity, footwear, and walking pattern
- Sensation, pedal pulses, Doppler waveforms, and blood-glucose control
An ankle-brachial index alone can falsely reassure when diabetes has calcified and stiffened the arteries. If arterial disease is suspected, ask about toe pressure or a toe-brachial index, plus skin-perfusion testing or transcutaneous oxygen measurement. A non-healing wound warrants vascular review even when pulses feel present.
The Wagner classification describes progression from a superficial ulcer to deeper involvement of tendon or bone, gangrene, and extensive tissue loss. Greater depth changes the plan: you may need stricter offloading, clinician-performed debridement, X-ray or MRI, vascular assessment, hospital treatment, or urgent surgical escalation. Sharp debridement must account for ischemia, bleeding risk, pain, and depth.
A diabetic wound specialist Kharadi service should assess these interacting causes, arrange vascular and orthopedic or podiatric review, manage infection, provide imaging and offloading, and track measurements over time—not only change dressings. A smaller-looking wound after cleaning does not prove healing.
Why does pressure relief matter as much as the dressing?
Pressure relief matters as much as the dressing because every step can drive a plantar ulcer into the ground again. Walking, a thick callus, a deformity, or unsuitable footwear concentrates force on one spot. After each dressing change, repetitive loading can reopen the wound, even when pain is absent because neuropathy reduces protective sensation.
- Reduce walking and keep weight off the wound as directed; continued loading delays closure.
- Use a removable cast walker when you can follow its use consistently and remove it only as instructed.
- For a suitable non-infected, non-ischemic plantar forefoot or midfoot ulcer, use a non-removable knee-high device such as total-contact casting when the clinician recommends it.
- Choose therapeutic footwear that redistributes pressure.
- A felted dressing can cushion a pressure point when other devices are unsuitable.
The clinician selects the device after checking infection, blood supply, balance, skin condition, and your ability to follow the plan. Sharp debridement and callus removal belong to a trained clinician, who considers ischemia, bleeding risk, pain, and wound depth while exposing the true size and removing mechanically harmful tissue.
For diabetic foot wound treatment in Pune, ask for assessment rather than dressing changes alone. A new hot, swollen foot is urgent: stop walking and seek assessment for Charcot neuro-osteoarthropathy, because weight-bearing can worsen structural damage.
When do infection tests, antibiotics, or imaging become necessary?
A diabetic foot infection is diagnosed from examination, not a positive superficial swab alone. Infection is supported by at least two local findings: swelling, erythema, warmth, tenderness, pain, or purulent discharge. A swab can grow colonising bacteria and misdirect treatment, so a clinically uninfected ulcer should not receive antibiotics to prevent infection or speed healing.
1. Seek urgent assessment for a deep abscess, necrosis or gangrene, severe ischemia, foul drainage, spreading redness, rapidly increasing swelling or pain, or systemic illness. These findings can require drainage, surgical debridement, intravenous treatment, vascular review, or hospital care rather than a routine dressing visit.
2. If bone infection is suspected, the clinician usually starts with a probe-to-bone test, then orders a plain X-ray to look for a foreign body or bone change. Blood tests such as C-reactive protein and erythrocyte sedimentation rate add inflammatory evidence; MRI is appropriate when concern remains after this initial assessment.
3. A bone sample for culture, with histology when needed, gives stronger evidence of osteomyelitis than a superficial swab. Soft-tissue infection often receives 1–2 weeks of antibiotics; 3–4 weeks may be considered for extensive or slow-resolving infection, or severe peripheral artery disease. Osteomyelitis requires specialist planning and longer treatment.
For diabetic ulcer treatment in Wagholi, ask whether the service can arrange imaging, vascular assessment, wound sampling, and urgent escalation instead of prescribing antibiotics from a swab result alone.
How should you compare diabetic wound services in Pune?
A diabetic wound care hospital in Pune should offer more than dressing changes. Ask these questions before choosing a service or arranging diabetic ulcer treatment in Wagholi:
- Is vascular assessment available, including Doppler or toe-pressure testing when needed?
- Does an orthopedic or podiatric clinician assess pressure points, deformity, footwear, and walking pattern?
- Can the team manage infection, arrange imaging, perform clinician-led debridement, and provide effective offloading?
- Can it escalate urgently for spreading infection, gangrene, severe ischemia, deep abscess, or systemic illness?
| Service | What to verify | Why it matters |
|---|---|---|
| Dressing-only clinic | Product changes without pressure or blood-flow assessment | The ulcer can reopen or deteriorate beneath a cleaner surface |
| Coordinated wound service | Vascular, orthopedic or podiatric, infection, imaging, debridement, and offloading access | Treats causes as well as the wound |
| Urgent-capable hospital | Same-day review, imaging, surgery, and escalation pathways | Delays can threaten tissue and limb |
Dressing changes are insufficient when pressure, ischemia, infection, deformity, kidney disease, smoking, poor nutrition, or uncontrolled glucose remains unaddressed. At every review, record length, width, depth, undermining, tissue type, exudate, perfusion, infection signs, and offloading adherence. A wound that looks smaller after cleaning has not necessarily healed.
If progress stalls, reassess the diagnosis, pressure, blood supply, infection, and systemic factors rather than endlessly changing dressings. Isha Trauma Care Hospital is a Wagholi orthopedic and trauma-care option for coordinated assessment, treatment, and rehabilitation.
Related service
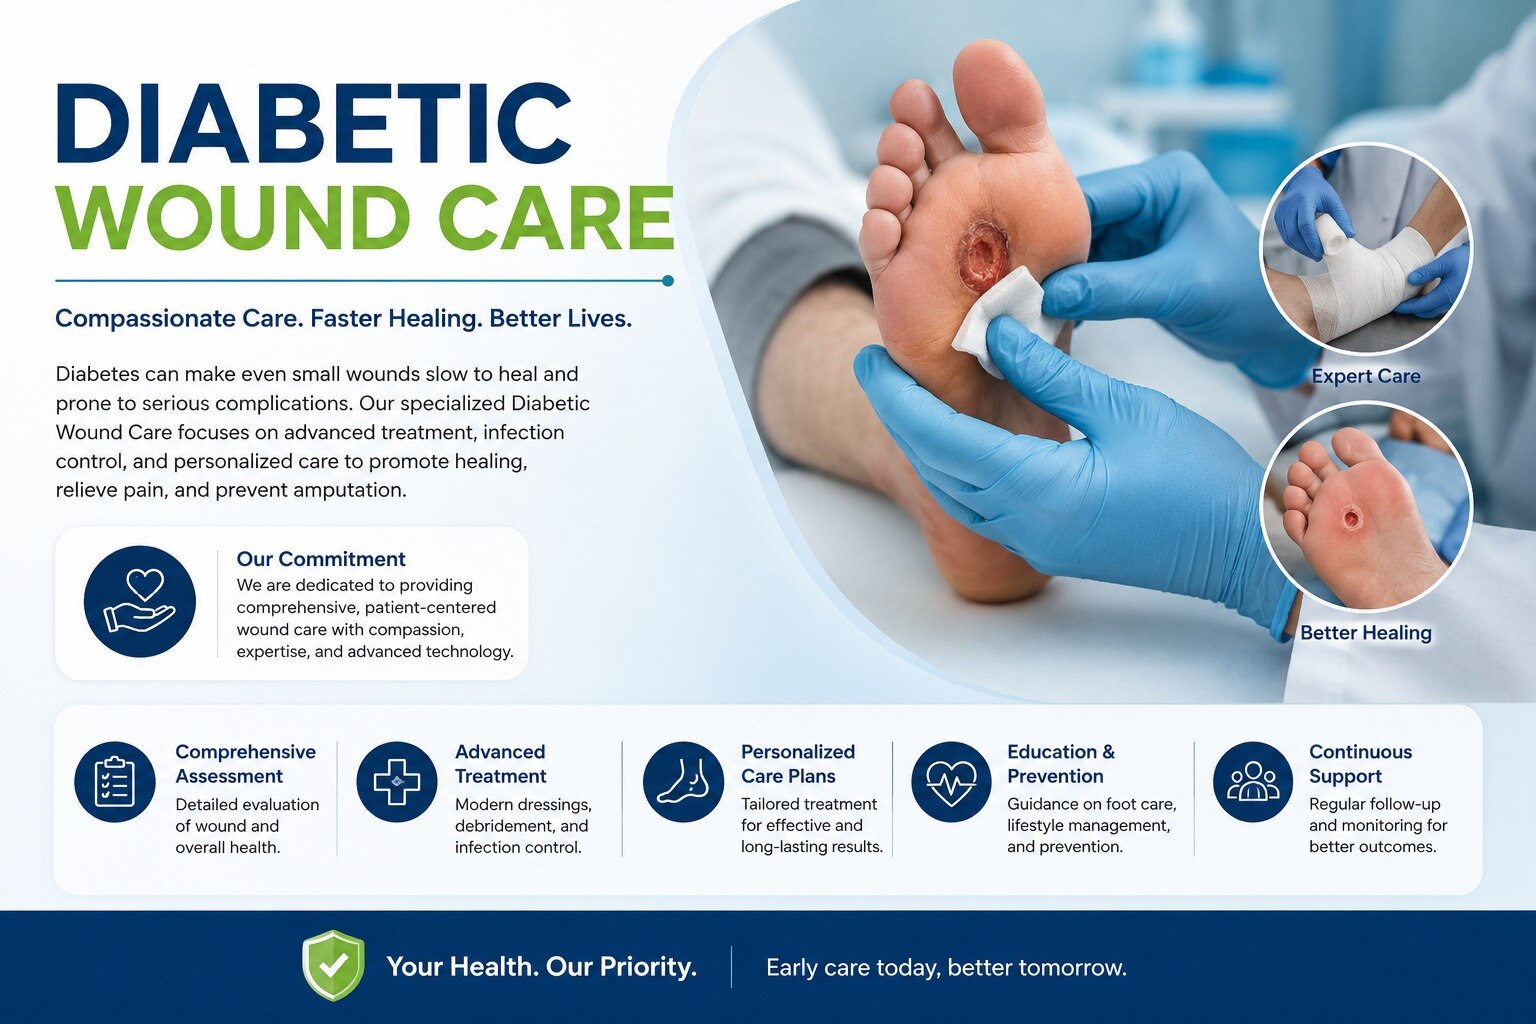
DIABETIC WOUND CARE ### Diabetic Wound Care Diabetic wounds require timely and specialized care to prevent infection and serious complications. View service → |
Frequently asked questions
Which diabetic foot wounds need medical attention today?
Seek same-day assessment when redness spreads, the skin feels warm or swollen, pus or foul odour appears, tissue turns black, red streaks travel up the foot or leg, pain increases, or a new wound develops over a bony prominence.
How does a clinician determine what is causing a diabetic foot wound?
The clinician examines the wound’s size, depth, tissue, drainage, surrounding skin, blood supply, sensation, footwear, and pressure points. They also review diabetes control, previous ulcers, injuries, and walking habits.
Why does pressure relief matter as much as the dressing?
Repeated pressure from walking, footwear, or a bony prominence can keep reopening the wound. Offloading removes that stress so the dressing and the body’s repair process can work.
When do infection tests, antibiotics, or imaging become necessary?
A clinician decides after examining signs such as spreading redness, warmth, swelling, drainage, odour, fever, deeper tissue involvement, or exposed bone. Tests, antibiotics, and imaging depend on the suspected infection and wound depth.
How should you compare diabetic wound services in Pune?
Check whether the service provides vascular and sensation assessment, wound cleaning and dressing, pressure offloading, infection evaluation, imaging access, diabetes coordination, and scheduled follow-up. Patients in Wagholi or Kharadi can also compare travel time and emergency access.